Alzheimer's disease is one of medicine's most stubborn puzzles. Two patients can carry the same diagnosis, score similarly on the same memory tests, and still differ enormously in which brain cells falter first, which molecular pathways go awry, and how quickly decline follows. A study published online in Nature Medicine on 23 September 2026 argues that artificial intelligence can help make sense of that variability at a scale earlier methods could not reach.
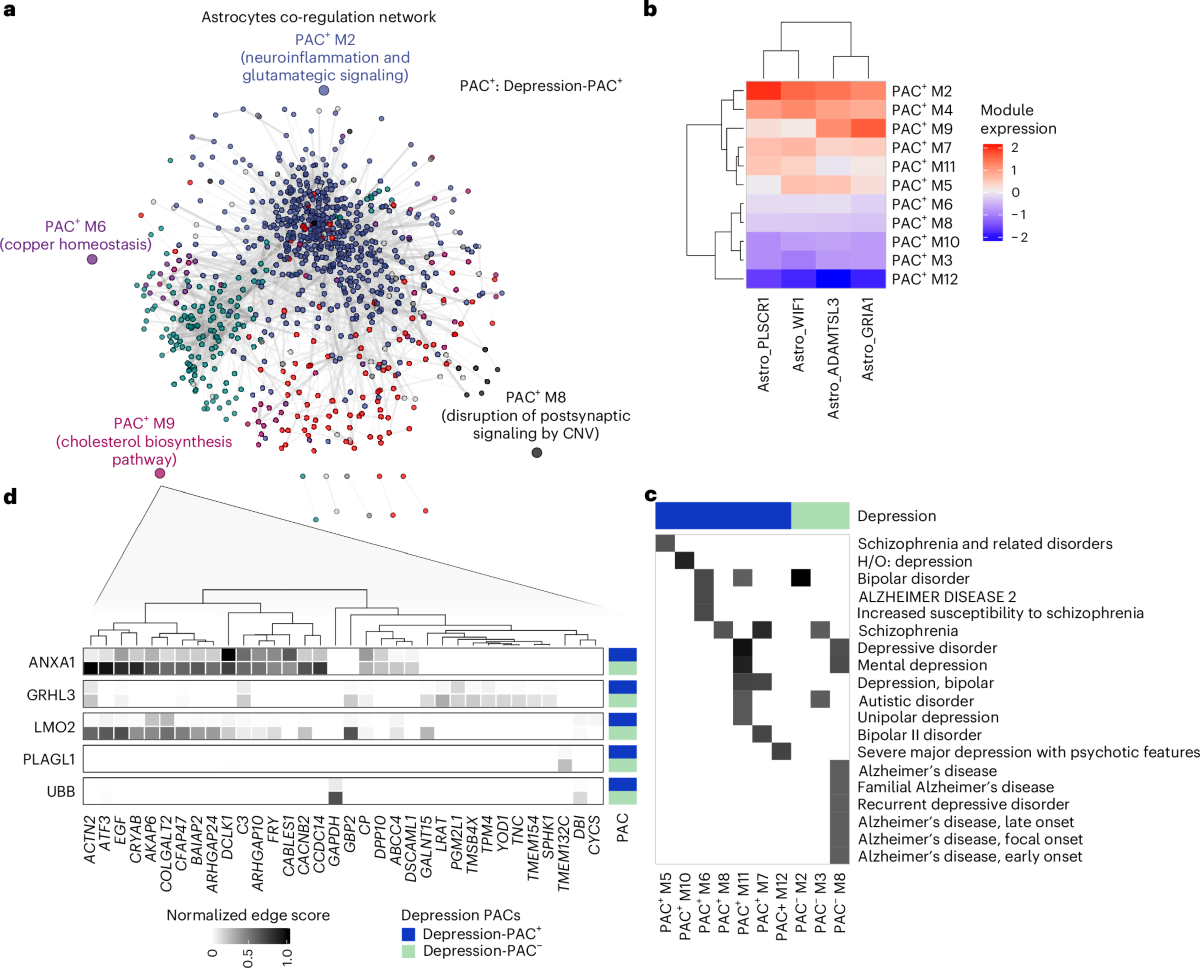
The paper, titled "AI-based characterization of Alzheimer's disease phenotypes from population-scale single-cell data," applies machine-learning analysis to single-cell measurements drawn from a cohort of 584 brain donors — a group that includes patients with Alzheimer's disease alongside comparison donors. The stated ambition is easy to describe and hard to execute: rather than treating Alzheimer's as a single uniform condition, use computational methods to sort the molecular profiles of individual cells into recognizable disease phenotypes.
Why Bulk Brain Tissue Blurs the Picture
For most of the history of Alzheimer's research, scientists have studied brain tissue in bulk. Grind up a region of cortex, measure the average activity of thousands of genes across millions of cells, and you get a clean, reproducible number. But an average is a poor description of a neighborhood. If a small population of immune cells is mounting an inflammatory response while most neurons are simply going about their business, that signal can be diluted into invisibility. The same problem runs in reverse: a measurement dominated by the most abundant cell type can mask the behavior of everything else.
Single-cell technologies changed the arithmetic. Instead of one measurement per brain region, researchers can now capture gene activity in thousands of individual cells or nuclei at once, giving each one a molecular identity. The result is not a single curve but a vast, sparse matrix of cells and genes — a dataset whose sheer size is precisely what makes machine learning attractive.
The cell types that dominate the conversation
- Neurons carry the electrical and synaptic machinery that memory depends on, and their selective vulnerability in different brain regions is a defining feature of the disease.
- Astrocytes support neuronal metabolism and help maintain the blood-brain barrier, and they can shift into reactive states that either protect or harm surrounding tissue.
- Microglia are the brain's resident immune cells; their activation states are among the most heavily studied variables in Alzheimer's research.
- Oligodendrocytes and their precursors wrap axons in myelin, and changes in white-matter support can alter how quickly neural circuits communicate.
- Vascular and barrier cells line the brain's blood supply, where leakage and impaired clearance mechanisms have long been implicated in disease progression.
What AI Actually Contributes
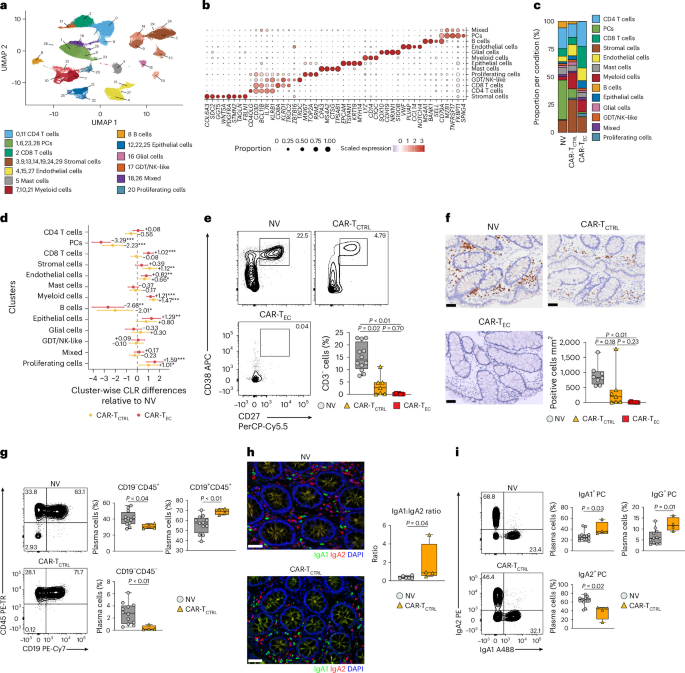
Once a dataset contains hundreds of thousands of cells, each described by thousands of genes, no human can eyeball it. Machine-learning methods are used to compress that dimensionality, group cells with similar profiles, and search for structure that cuts across conventional categories — for instance, cell states that sit between two known types, or donor-level patterns that only emerge when hundreds of individuals are compared at once.
The word "characterization" in the paper's title matters. This is not a claim to have built a diagnostic test, nor a promise that a model can predict who will develop Alzheimer's. It is descriptive and organizational work: taking a highly heterogeneous disease and asking whether its molecular presentation resolves into a smaller number of coherent phenotypes that can be named, compared, and eventually targeted.
The Weight of 584 Brain Donors
Human brain tissue is a scarce resource. Donor programs require years of coordination with families, clinicians, and pathologists, and every specimen arrives with its own history of age, genetics, medication, and postmortem interval. Assembling a cohort of 584 donors is therefore a substantial logistical achievement in its own right, and it is the phrase "population-scale" in the title that signals why the study can attempt something a small sample could not.
Scale buys statistical power. Rare cell states, subtle shifts in the proportion of one cell type relative to another, and interactions between genetic risk and cell behavior all become detectable only when enough donors are compared. It also enables the kind of internal replication that machine-learning studies need: a pattern found in one subset of donors can be tested against another before anyone claims it is real.

Why Phenotypes Matter More Than a Single Label
Alzheimer's drug development has been shaped by the assumption that one disease requires one mechanism and one treatment. That assumption has produced decades of expensive disappointment. If the condition is in fact a family of related but distinguishable molecular phenotypes, then averaging outcomes across all patients could hide genuine benefits in a subgroup — and could equally expose patients to side effects from a therapy aimed at the wrong biology.
Phenotype-first thinking is not new in oncology, where tumor profiling is standard practice before treatment selection. The question this line of research poses is whether neurodegeneration can be approached the same way, using cellular and molecular signatures rather than clinical symptoms alone to define who a patient is.
Limits and Open Questions
Postmortem tissue offers a snapshot, often taken at the end of a long illness. It can reveal which cellular states accompany advanced disease, but it cannot easily establish which changes came first or which are causes rather than consequences. Donor cohorts also skew in ways that are well known to researchers: the people who donate brains are not a random sample of the population, and the disease itself may alter cellular profiles in ways unrelated to its root cause.
There is also the familiar hazard of applying powerful models to complex biology. Machine learning can find structure that reflects technical artifacts — differences in how samples were processed, or in how cells were sequenced — rather than disease. Independent replication in separate cohorts, and validation with complementary methods, is what separates a compelling pattern from a durable finding.

What to Watch Next
- Replication: whether the same phenotypes reappear in independent donor collections and in living patients sampled through blood or cerebrospinal fluid.
- Spatial context: whether cell states identified in dissociated tissue can be mapped back to their physical neighborhoods, since location shapes function.
- Clinical translation: whether any phenotype corresponds to a measurable difference in progression or response to treatment.
- Data sharing: whether the underlying cellular data are released in a form other groups can reuse, which determines how quickly the field can build on the result.
The published summary of the study is deliberately compact, and the substantive detail — which phenotypes emerged, how stable they are, and how they relate to existing genetic and pathological markers — lives in the full paper. What the summary does establish is the shape of the effort: an AI-driven attempt to replace a single, blunt Alzheimer's label with a more precise cellular description, applied at a scale that was not possible a decade ago. Whether that description holds up will be decided by replication, not by the elegance of the model.
This article is based on reporting by Nature Medicine. Read the original article.
Originally published on nature.com